

AI has a genuine foothold in medicine, in reading scans and flagging abnormalities. The fight now is over everything beyond that, and doctors are not simply going along with it.
As vendors sell AI tools for tasks past radiology and diagnostics, clinicians are resisting adoption, and their stated reason is specific: there is limited real-world data showing these broader tools actually work.
The Evidence Gap

Imaging AI earned its place partly because its performance could be measured against a clear answer — the scan is either read correctly or it is not.
Tools that move into messier territory, such as suggesting treatments or drafting clinical decisions, are harder to validate and, so far, less validated. Clinicians are asking for the evidence before they rely on the tool, which is exactly the standard the rest of medicine is held to. Vendors selling beyond radiology are, in the words of the reporting, hitting a clinician wall on evidence.
The Two Fears The Survey Found
Trending Stories

Nigeria: Protesters take to the streets, police fire shots

US-Iran war: Tehran draws red lines — seven demands before any peace talks

Russia-Europe tensions: Polish PM warns Russian attacks could test NATO's unity

‘Not the US or China’: These are the countries leading the world in arable land

EXCLUSIVE | Singer Hanita Bhambri on her Toxic debut, working with Vishal Mishra and more

Mark Carney mimics Trump in hilarious moment over C$70 billion clean-energy investment; room erupts in laughter

Delhi voter roll shake-up: 3.31 million electors flagged in SIR review

Aravana prasadam shortage at Sabarimala temple in Kerala triggers protests, TDB questioned

‘End of my career...’: NSA Doval recalls tense Sikkim mission when China captured Indian intelligence team

Report: Iran rebuilding Taleghan 2, nuclear site tied to past weapons research, hit twice by Israel

Trump defends AI amid growing alarm, announces new 'AI force' and promises an 'AI czar'

Iran sets 7 conditions to end war with US: What are Tehran’s demands?

Trump announces ‘AI Force’ as debate grows over AI risks and regulation

China may have gained access to US's classified F-35 jets; parts meant for repairs diverted to Hong Kong, sparking Pentagon inquiry

Gaza under attack: Health chief's son killed in IDF strikes

Man breaks open wall hiding hundreds of books since 15 years

Arvind Kejriwal, family members, Delhi CM Rekha Gupta get SIR notices

AI actress Tilly Norwood glitches mid-interview, switches from English to Chinese | Watch

Saudi vs Houthis: Houthis claim missiles & drones used in attack on key Saudi sites

Ed Sheeran addresses Macklemore's removal, Gaza conflict during Philadelphia concert: 'I cannot hide how I feel'

Nepal forms 7-member panel to probe August 26 Bhotekoshi flood from source to downstream

‘Will go to any extent’: Pakistan vows to defend Saudi Arabia amid Houthi attacks
66 years of the Indus Waters Treaty: How India and Pakistan settled a bitter river dispute

The Verdict | When precision fails: US commits war crime in Minab school strike, UN finds

9 women found dead near Johannesburg: South Africans rally, demand 'enough' to femicide

Kampala-Ankara rift deepens: Uganda suspends military ties, seeks Fred Lumbuye's extradition

Several petrol pumps, other businesses to refuse UPI payments above Rs 2,000 from Oct 16: Is it legal?

US-Iran war: Tehran sets seven conditions to re-engage in talks with US

Reacher star Alan Ritchson opens up about alleged blackmail, suicide attempt during difficult period
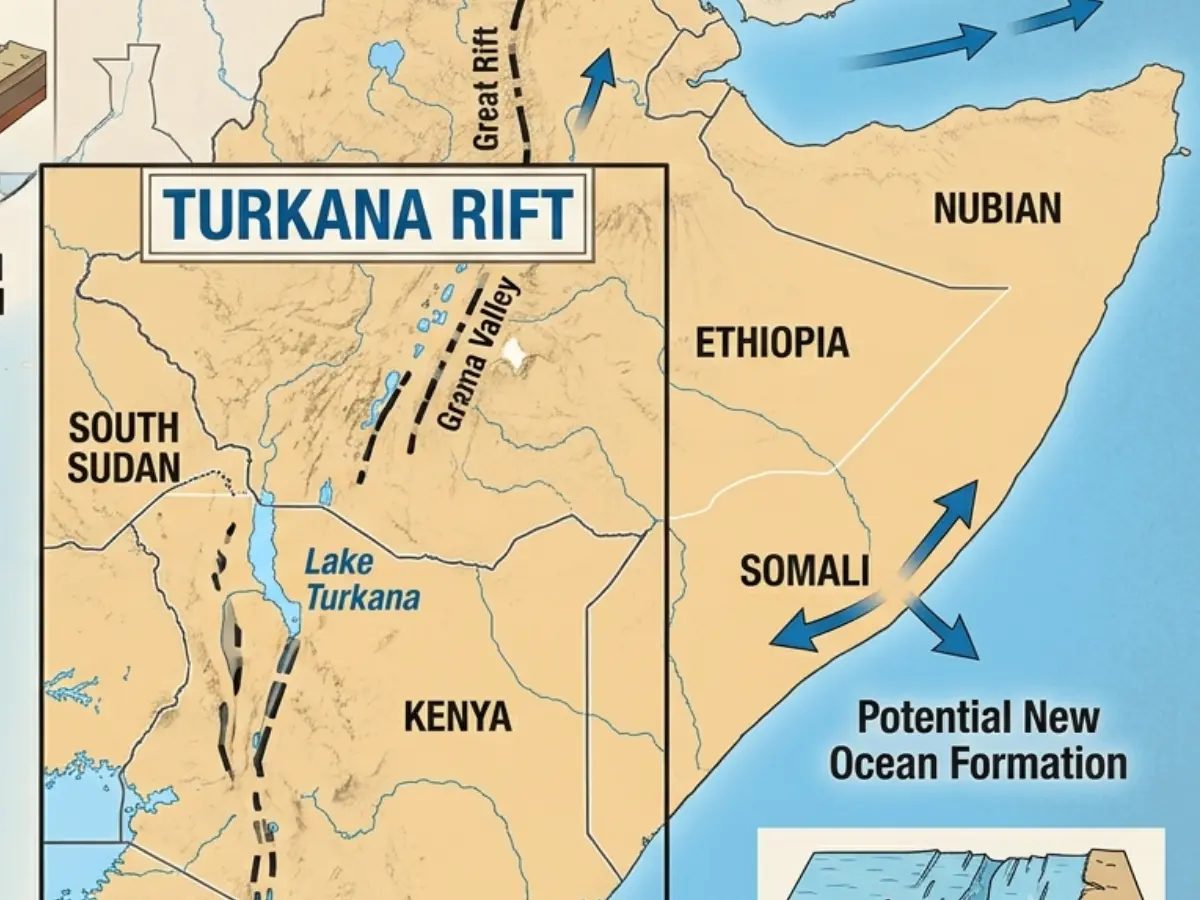
Africa is splitting, and a lot sooner than estimated, giving way to a new ocean

Flying cars in UAE: Ras Al Khaimah signs deal with Chinese company to test new transport

West Indies Squad for India Series: Hetmyer included for T20Is, Holder rested

Trump bans CNN, MS NOW and Politico from White House over ‘FAKE NEWS’

Trump 2.0: Dark days ahead for America’s ‘imperial presidency’

How many F-35s does Britain, Japan and Israel have?

Harry Brook targets long reign at top of T20I rankings after Sri Lanka sweep

Russia's deadly Ukraine strikes kill 2 in Sumy, hit Dnipro mall

Russia holds first parliamentary elections since the beginning of the Ukraine war

Meet top 5 Indian batters with fastest T20I centuries

A 2026 survey of US doctors and nurses put numbers on the discomfort, and two figures stand out, both at 74 per cent.
The first is 'deskilling': 74 per cent worried that leaning on AI erodes clinicians' own abilities — including the ability to notice when the AI is wrong. The second, also 74 per cent, is hallucination: the concern that AI invents incorrect information, such as fake medical studies, and presents it confidently.
Those two fears compound each other. A tool that occasionally fabricates is dangerous in proportion to how much the humans checking it have let their own judgement atrophy. The more a clinician relies on the AI, the less equipped they are to catch the moment it fails.
Why The Caution Is Rational, Not Reactionary
It would be easy to frame this as doctors resisting change. That framing is wrong, and worth correcting.
Medicine has a professional and legal duty to demand evidence before adopting an intervention, precisely because the cost of being wrong is measured in patients. Requiring proof of effectiveness from an AI tool is not technophobia; it is the same bar a new drug or device has to clear. The burden sits with the vendor to show the tool works, not with the clinician to show it does not.
The Other Side
There is a real cost to excessive caution too, and honesty requires naming it.
Some of these tools may genuinely help — reducing paperwork, catching drug interactions, freeing clinicians for patient contact. A blanket wall of scepticism could keep useful tools out as effectively as it keeps unproven ones out, and patients bear that cost as well. The reporting suggests the resolution is not a yes or no but a sequence: the hospitals that publish real-world validation and set up governance first will earn clinician trust, while those that skip that step stall in procurement.
In other words, the evidence wall is not a permanent barrier. It is a bill coming due for tools that were sold ahead of their proof.
What To Watch
Whether vendors invest in the clinical trials and real-world studies that would clear the evidence bar, rather than marketing around it. Whether hospitals build the governance frameworks that let them adopt AI accountably. And whether deskilling is taken seriously as a design problem — building tools that keep clinicians sharp rather than sidelining them — because that risk grows precisely as the tools get good enough to trust.
